International health insurance for American digital nomads
Your home cover does not follow you abroad
US employer, ACA and Medicare plans almost never cover living abroad. Routine care outside the United States is generally not covered. Emergency care abroad, when it pays, is out-of-network reimbursement. International health insurance is the product that follows you; travel insurance only fits a trip that still ends.
Travel vs health once you leave
A domestic plan does not become travel insurance, and travel insurance does not become international health cover.
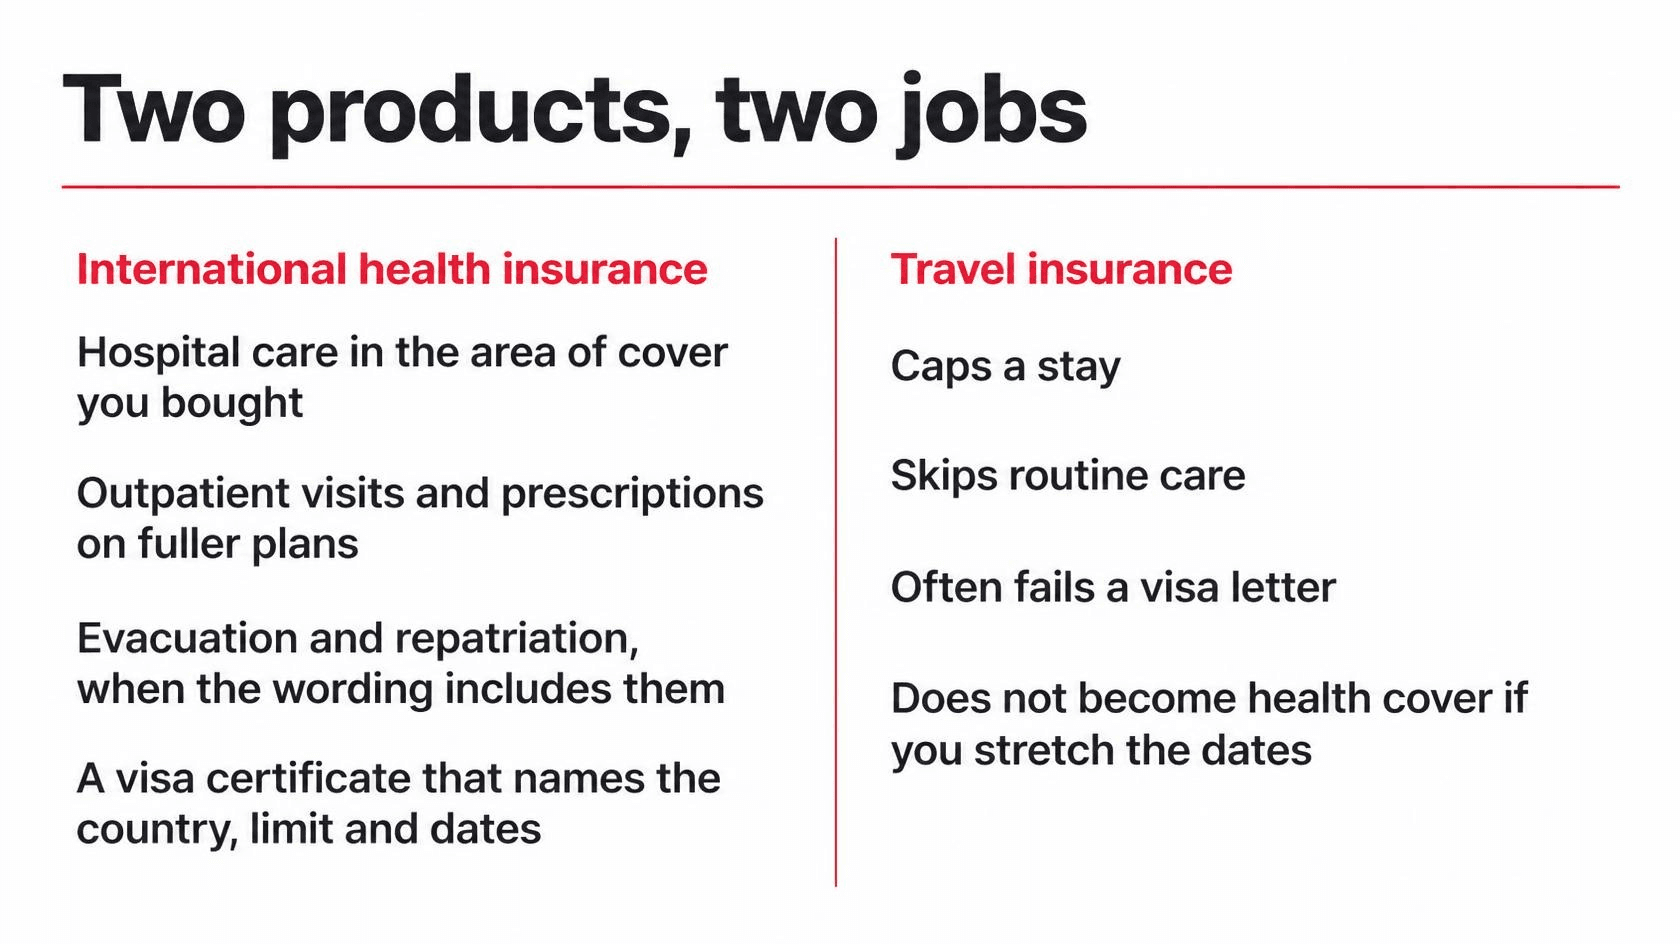
The difference is set out in our guide to nomad health insurance. Use the table, then the essay below.
Travel insurance versus nomad-style cover versus international health insurance
Duration
- Travel
- Trip that ends; often 30–90 days per stay
- Nomad-style
- Continuous, renews while you are away
- International health
- Annual, portable across countries
Routine care
- Travel
- No
- Nomad-style
- Rarely
- International health
- Yes, if outpatient is in the plan
Pre-existing
- Travel
- Usually excluded
- Nomad-style
- Usually excluded
- International health
- Underwritten
Home country
- Travel
- Stops when you land
- Nomad-style
- Usually excluded
- International health
- Optional region
Visa-ready
- Travel
- Often rejected
- Nomad-style
- Sometimes
- International health
- Usually, unless a local insurer is required
Evacuation
- Travel
- If listed
- Nomad-style
- Usually
- International health
- Should be included
| Attribute | Travel | Nomad-style | International health |
|---|---|---|---|
| Duration | Trip that ends; often 30–90 days per stay | Continuous, renews while you are away | Annual, portable across countries |
| Routine care | No | Rarely | Yes, if outpatient is in the plan |
| Pre-existing | Usually excluded | Usually excluded | Underwritten |
| Home country | Stops when you land | Usually excluded | Optional region |
| Visa-ready | Often rejected | Sometimes | Usually, unless a local insurer is required |
| Evacuation | If listed | Usually | Should be included |
How long your home cover lasts abroad
Plan-specific.
Some employer business-travel riders cover international trips of up to six months. Standard US group plans treat routine care abroad as non-covered entirely, and emergency-only windows vary by plan. Read your own Summary of Benefits and Coverage for the exact number.
What breaks when you leave
No routine care abroad: no annual physical, no chronic-disease management, no prescription refills, no specialist visits.
Emergency care abroad is reimbursable under most group plans, but only as out-of-network, meaning you pay the foreign hospital upfront in cash or credit card, submit documentation (translated to English at your cost), and wait weeks to months for partial reimbursement.
What you need instead
For trips under ~6 months: a dedicated travel-medical policy alongside your US employer plan (keep COBRA / employer plan running for US continuity).
For trips over 6 months or open-ended nomadism: a full international IPMI plan and a deliberate decision about whether to also keep COBRA, usually only worth it for pre-existing conditions or imminent return.
Common mistakes
- Assuming COBRA extends coverage abroad; it doesn't, COBRA is the same US-domestic plan
- Assuming Medicare follows you abroad; Original Medicare does not cover care outside the US except in narrow border-region edge cases
- Buying a cheap travel-medical subscription, then discovering routine care isn't covered
- Cancelling the US employer plan before securing the international plan, which leaves an underwriting gap if you have pre-existing conditions
- Not declaring the move to the US plan, then losing reimbursement on the one emergency claim because the carrier views the trip as a relocation
- Choosing reimbursement-only cover for Bali, Bangkok, or CDMX where private hospitals demand cash deposit on admission
How American cover really treats a leaver
US group health plans typically do not cover routine care abroad and cover emergency care only for plan-specific windows: some employer business-travel riders, for example, cover trips of up to six months, while standard group plans treat routine care abroad as non-covered entirely.
For anyone under 65 there is no national health system to lose.
US coverage is private and tied to a domestic plan: an employer group plan, an Affordable Care Act marketplace plan, or COBRA. None of these is a government scheme that follows you overseas, and every one is built around a US provider network, so care abroad falls outside it by design.
Employer and ACA marketplace plans are domestic-network products. Marketplace plans are sold state by state and many use narrow regional networks, so some will not even fully cover you in a neighbouring state. HealthCare.gov describes marketplace coverage as care from doctors, hospitals and providers within the US. A plan might reimburse a genuine emergency abroad at out-of-network rates, but routine care once you have moved, a check-up, a prescription refill, managing a chronic condition, a specialist visit, is generally not covered at all.
COBRA is not a fix. It only lets you keep your existing employer plan for a period after leaving the job, and by federal law the coverage is identical to the active-employee plan: same network, same limits. So it carries exactly the same domestic-only gap, just at a higher premium because you now pay the full cost yourself.
Medicare, for those 65 and over, almost never pays outside the US. Medicare.gov lists only three narrow exceptions, all emergencies tied to being in or passing through the US: a medical emergency in the US where a foreign hospital is closer, an emergency while travelling the direct route through Canada between Alaska and another state, and care at a foreign hospital that is closer to your US home than any US hospital. None of these apply to someone living abroad. Dropping Part B while overseas is also a costly trap on the way back: the late-enrolment penalty adds 10% to your Part B premium for each full 12-month period you could have had it but did not, and once it applies you pay it for as long as you have Medicare, so a few years abroad without a qualifying exception can raise your premium for the rest of your life.
The return is handled through the marketplace. Moving back to the US from another country is a qualifying life event that opens a Special Enrollment Period, and you generally get 60 days from the move to choose a plan. Two catches matter: a move only for vacation or medical treatment does not qualify, and HealthCare.gov usually will not let you complete this particular enrolment online, so you have to phone the Marketplace Call Center. Coverage is not backdated, so any gap between landing home and your new plan starting is uninsured.
An HSA or FSA is not coverage, and it does not solve this either. There is no geographic bar in IRS Publication 502: qualified medical care counts even when you receive it in another country, so HSA money can legally reimburse a foreign doctor visit or prescription. The problem is practical. No foreign hospital or pharmacy bills your HSA, and many HSA debit cards are blocked on international transactions, so in reality you pay the provider in cash or on a card and reimburse yourself afterward, keeping dated, translated receipts and exchange-rate records. An FSA is worse for a nomad because it is use-it-or-lose-it within the plan year and tied to your employer. These are tax-advantaged ways to spend your own money, not a network that pays a provider on your behalf.
For lower-income Americans, Medicaid is even more locked to home. It is administered state by state, and you have to be a resident of the state you are enrolled in. It pays nothing outside the US, there is no version that travels with you, and there is no mechanism to transfer it between states, so leaving the country ends any practical use of it. If you move abroad and later return, you generally have to reapply, in whichever state you land in.
It is worth being precise about what an emergency being covered means in practice. Even where a domestic plan will consider a foreign emergency, the foreign hospital has no relationship with your US insurer and will not bill it. You pay the bill yourself, often upfront or on discharge, then file a claim and hope to recover part of it at out-of-network rates. Because the provider is out of network there is no negotiated price and none of the balance-billing protection you would have at home, so you can be left owing whatever the insurer declines to reimburse. A genuinely covered emergency still means producing cash or a working credit card at the point of care.
One narrow federal program does follow you abroad, but only for a specific group. The VA Foreign Medical Program reimburses care received in another country, and it is real, but it only covers a VA-rated, service-connected disability, or a condition that aggravates one. It does nothing for the ordinary illnesses and accidents that make up most medical spending, so even for veterans it is not general health cover overseas.
Our take
For Americans, the cleanest pattern is: keep the US employer plan running for the first 90 days abroad (it overlaps with most carriers' emergency window), layer travel-medical on top, and only switch to a full international IPMI once you commit to staying out for 6+ months.
The decision point that matters most is pre-existing conditions: if you have any, never let coverage lapse between policies.
FAQ
Only if you accept that almost nothing abroad will be covered. COBRA continues your US employer plan; it does not add international coverage. Use COBRA for US-side continuity and pair it with a real international plan for the country you're actually in.
Original Medicare (Parts A and B) does not cover health care received outside the US, with narrow exceptions for medical emergencies near US borders. Some Medigap policies (C, D, F, G, M, N) include limited foreign-travel emergency coverage, typically 80% reimbursement up to a $50 000 lifetime cap, with a deductible. For sustained time abroad, you need a separate international plan.
Heavily dependent on whether the policy includes US coverage. Plans that exclude the US are dramatically cheaper than worldwide-including-US plans. Request specific quotes from the matching form; fair ranges are wide enough that a published number would mislead.
If you're physically outside the US for 330+ days in any 12-month period, you're considered to have minimum essential coverage and the ACA individual-mandate considerations don't apply. Under that threshold, depending on residency status, US tax-side coverage rules may still apply, so talk to a tax professional, not to us.
This page is the origin-country gap. It is not a passport ranking and it does not quote a premium. How we measure cost.
Find cover that actually follows you
The form asks about health and the visa. You get one offer by email. You pay the standard premium.
Get a quoteGoing for good rather than for a while? What US citizens lose by leaving, and what FATCA has to do with it
Typical destinations from here: Mexico, Portugal, Thailand, Spain and Colombia. The entry rule that actually asks for cover is the Temporary Resident Visa (Residente Temporal) and the D8 Digital Nomad Residence Visa. Which product fits is the insurance choice, and whether you clear a threshold is the which nomad visa check.
Get a quote in 3 steps
- 01
Fill out
The form only asks what changes the plan.
- 02
Get a quote
We compare the panel against your route, stay and visa.
- 03
Decide on the offer
If it fits, you take the policy out with the insurer. We are not the insurer.
Have a look if this page was not the question you came with.